🍪 We use cookies
We use cookies to enhance your experience, analyze site traffic, and for marketing purposes. By clicking "Accept All", you consent to our use of cookies. Read our Privacy Policy

The underlying pathology in medial tibial stress syndrome (MTSS) is bone overload. There are many different theories that purport to explain MTSS, but the bone overload theory is strongly supported by recent evidence.
We must understand the mechanism of bone stress injury and bone healing to manage and treat medial tibial bone syndrome (MTSS).
Bone remodels itself when there is damage to the bone. Remodeling is the sequential activity of bone-dissolving osteoclasts that remove the damaged bone, followed by osteoblasts that lay down bone-forming cells at the site of damage, fill the void, and form the base for new bone.
Bone stress injury indicates that the load-induced accumulation of micro-damage has outpaced the remodeling process of the bone. In the case of bone stress injury, a more porotic region appears at the site where the damage has outpaced the remodeling. In contrast to osteoporosis, where there is a general bone porosity, in bone stress injury, a specific region of the bone becomes porous because of the accumulated micro-damage and abruption in remodeling because of constant loading on that region of the bone. It makes the bone weak and reduces its ability to withstand the forces and loads imposed on it, which can lead to the stress fracture (1).
 Reproduced from Warden et al., 2021.
An accurate and reliable diagnosis can help clinicians makes a good foundation to discuss the patient’s expectations and develop an effective treatment plan.
Yates’s criteria for diagnosing MTSS are given below:
 Reproduced from east vic park physiotherapy
*We recommend rotating your phone to watch the videos*
We as clinicians must consider every possibility while examining a patient presenting with medial tibial pain. One of the most important differential diagnoses is the medial tibial stress fracture.
So how do we rule out medial tibial stress fracture?
A study by Charles Milgrom and colleagues in 2021 presented the guidelines for diagnosing the medial tibial stress fracture (3). The tibial stress fracture is more likely with the following presentation:
*We recommend rotating your phone to watch the videos*
Self-reported pain scores are not predictive of the medial tibial stress fracture. MRI is the most sensitive and specific and is the gold standard for diagnosing medial tibial stress fracture (4).
Fredericson et al, classified medial tibial stress syndrome based on the MRI findings (5). This classification system is used to estimate the delay in return to impact activity after MTSS. The grades of classification are depicted in the image, and the expected return to impact activity is given below based on these grades:
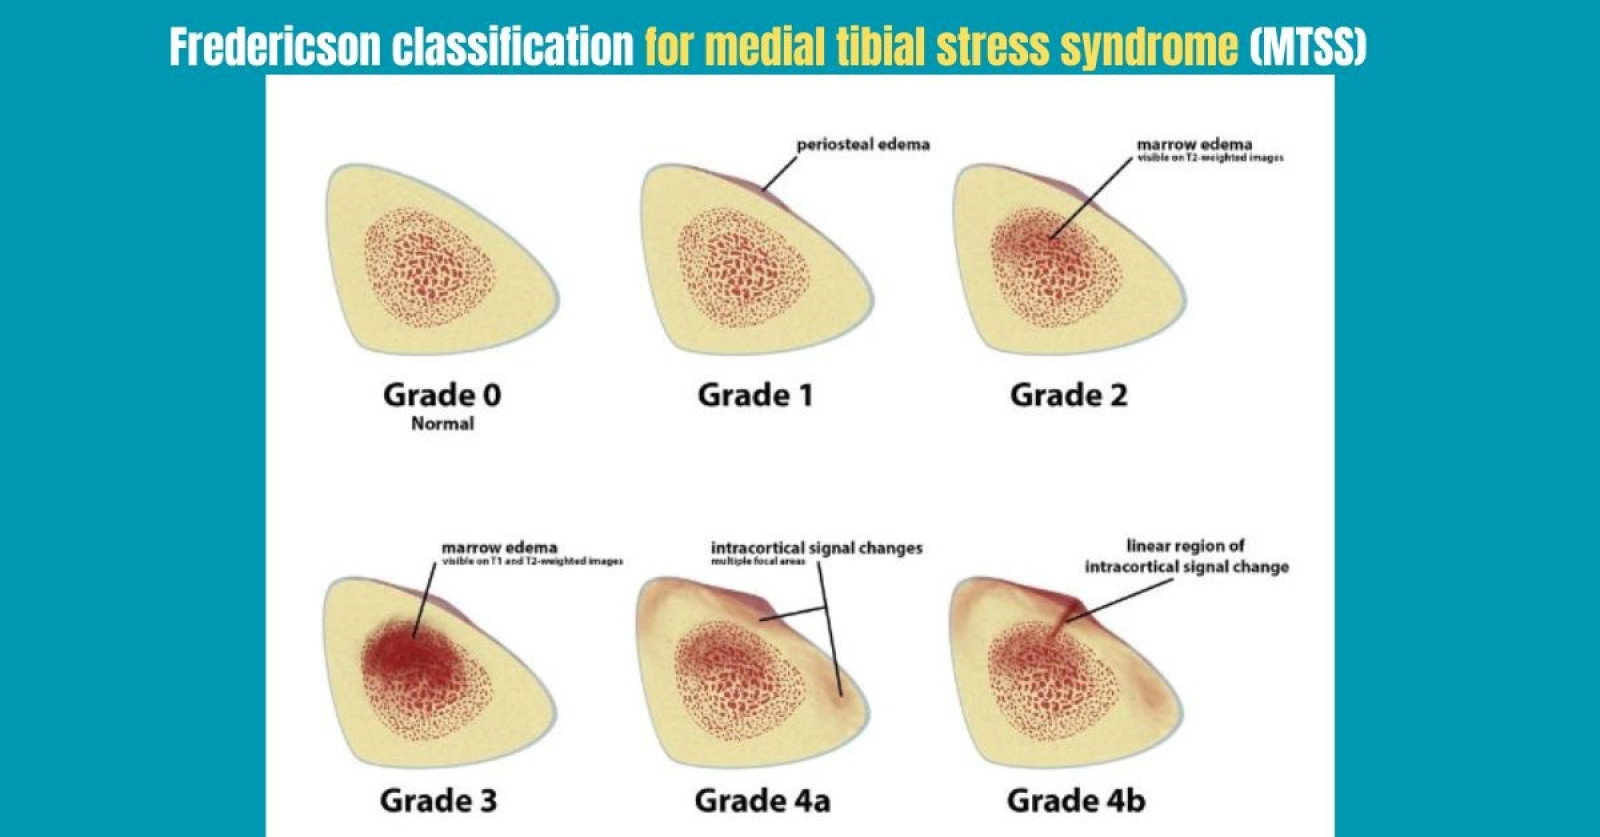 Reproduced from Radiopedia.org
ESTIMATED RETURN TO IMPACT ACTIVITY BASED ON THE FREDERICSON CLASSIFICATION SYSTEM (6)
Warden et al, in 2021, put forward the key principles for medial tibial stress syndrome (MTSS) management, which include the following (7):
When it comes to loading a bone with stress injury, a clinician should look for pain-free loading. In the case of bone stress injury, the remodeling process is already outpaced by the damage, and any extra load will add up to that damage, further hindering the healing and remodeling process and leading to the weakening of the bone and the potential for stress fractures. So pain-free loading is essential in individuals with a bone stress injury.
Cross training
Energy availability
The key muscles to address in athletes with medial tibial stress syndrome (MTSS) are calf complex muscles, glute, and quadriceps. The calf complex includes gastrocnemius and soleus. The deficit in the calf complex can increase stress on the tibia leading to more disruption in the healing process.
The other key muscles to address in individuals with MTSS include the glutes, hip abductors, and quadriceps muscles. These muscles stabilize the hip and take most of the body weight. If there is a strength deficit in these muscle groups, increased body weight can be transferred through the tibia, causing stress injuries.
So if a patient comes with MTSS, we need to address these muscle groups and build strength if necessary to help reduce the stress through the tibia and allow the stress injury to heal.
Before recommencing running consider the following:
We as clinicians should focus on the bigger picture and look for ways to reduce the risk of a subsequent injury. We might consider the following for this purpose:
REFERENCES

Bringing high-quality classes so you can help your patients better. Learn from the world's leading experts, from the comfort of your home. Staying up to date has never been easier.
© 2026 TrustMe. All rights reserved.
We usually answer within a minute.
Ask anything about your membership, certificates or what is in the library.